A 2021 Newcastle University study revealed that patients with lumbar disc disease who used inversion therapy faced a 21% surgery rate over two years, compared to 39% in matched controls who received standard care. This finding challenges the assumption that clinical traction automatically outperforms home-based inversion methods. The debate between Inversion Tables vs. Traction Therapy: Which Spinal Decompression Method Delivers Better Results? centers on efficacy, cost, and patient selection—not marketing promises.
Think of spinal decompression like stretching a compressed spring: inversion tables use gravity to pull the spring apart uniformly, while clinical traction applies precise, measured force to specific coils. Both methods aim to create space between vertebrae, but they achieve this goal through fundamentally different mechanisms.
Key Takeaways
- Inversion therapy reduced surgery rates by 46% in selected lumbar disc disease patients, according to Newcastle University research
- Clinical traction offers controlled, targeted decompression through motorized cycles, while inversion provides passive, gravity-based stretching
- Cost differences are substantial: inversion tables require $200-$500 one-time investment versus $2,000-$5,000 for clinical traction courses
- Safety profiles differ significantly: inversion increases skull and eye pressure, making it dangerous for glaucoma, hypertension, and cardiovascular patients
- Evidence quality remains mixed for both methods, with Cleveland Clinic rating inversion research as “limited and mostly small-study based”
Understanding the Core Mechanisms: How Each Method Works
Inversion Tables: Gravity-Based Passive Traction
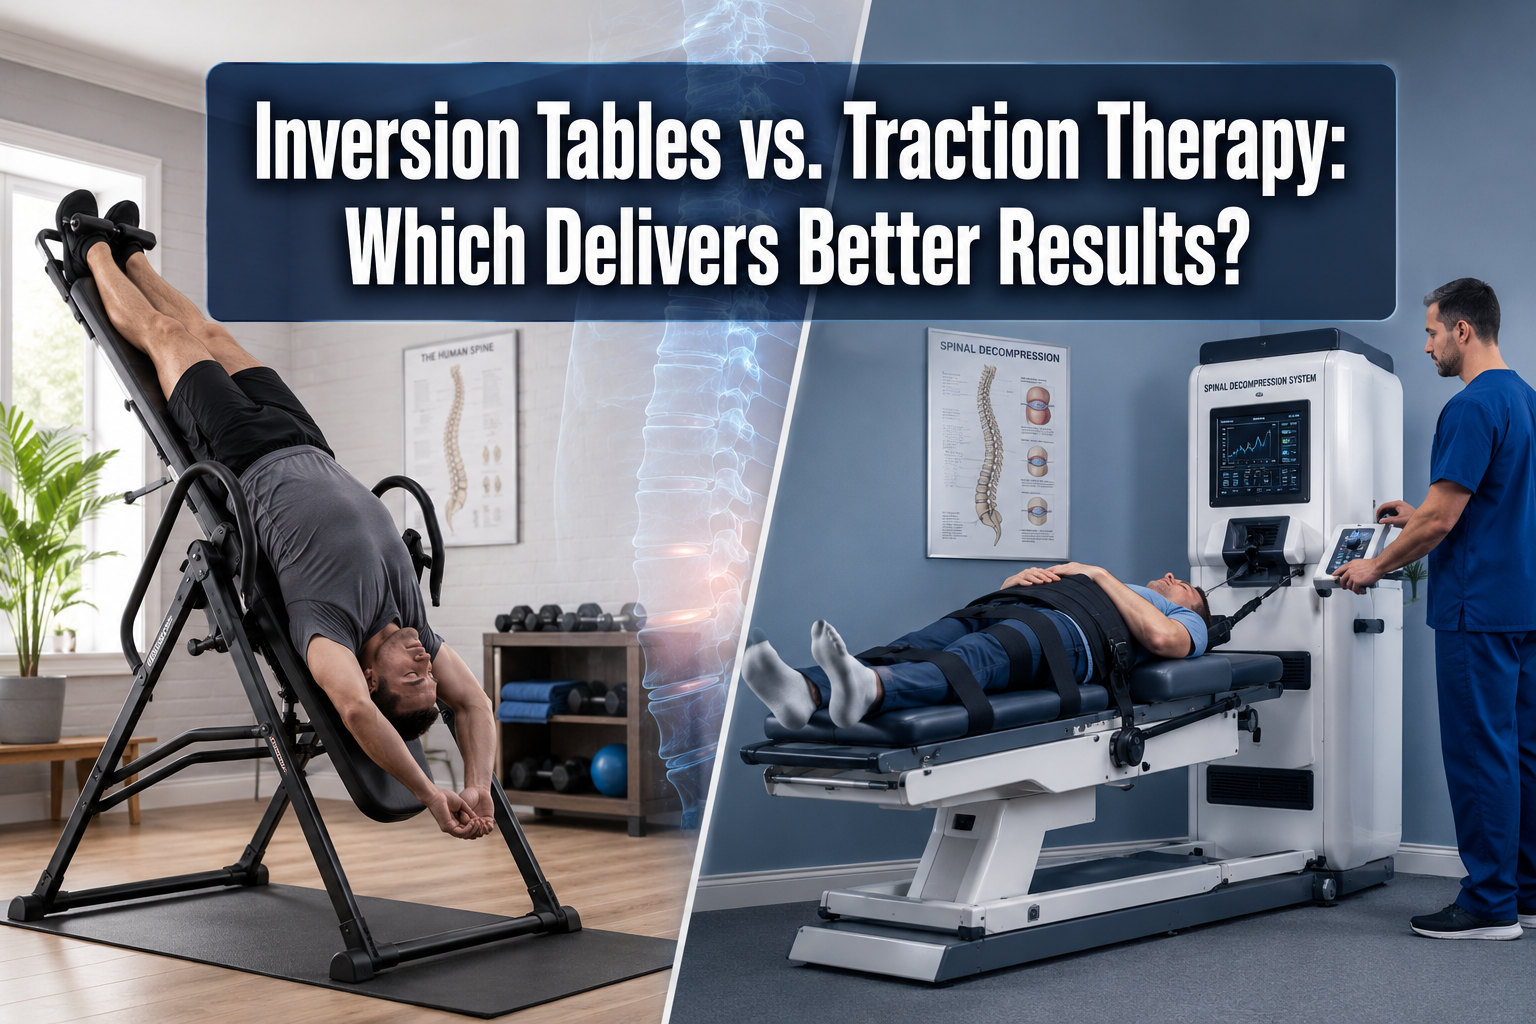
Inversion tables secure users by the ankles and rotate them to angles between 20 and 90 degrees. Gravity pulls the body downward, creating separation between vertebral discs. This passive approach requires no external motors or therapist intervention.
The decompression occurs uniformly across the entire spine. Users control the angle, duration, and frequency of sessions. Most protocols recommend starting at shallow angles (20-30 degrees) for 1-2 minutes and gradually progressing to steeper inversions over weeks.
Key characteristics:
- 🏠 Home-based, user-controlled sessions
- ⚖️ Uniform gravitational force across spine
- 📊 Static positioning without dynamic cycles
- 💰 One-time equipment purchase
- ⏱️ Flexible scheduling and duration
Clinical Traction Therapy: Motorized Controlled Decompression
Clinical traction uses specialized tables with computerized systems that apply measured pulling force to specific spinal segments. Therapists program decompression cycles that alternate between stretching and relaxation phases.
The motorized approach targets particular vertebral levels. Harness systems isolate the lumbar or cervical spine while the table applies controlled force. Treatment protocols typically involve 15-20 sessions over 4-6 weeks, with each session lasting 20-30 minutes.
Key characteristics:
- 🏥 Clinical setting with professional supervision
- 🎯 Targeted force to specific spinal segments
- 🔄 Dynamic cycles of traction and release
- 💵 Per-session fees or treatment packages
- 📋 Structured protocols with progress monitoring
Inversion Tables vs. Traction Therapy: Which Spinal Decompression Method Delivers Better Results? The Evidence
Clinical Efficacy: What Research Actually Shows
The Newcastle University study provides the strongest recent evidence for inversion therapy. Researchers tracked patients with lumbar disc disease and sciatica who were on surgical waiting lists. The inversion group demonstrated both symptom improvement and reduced surgical intervention rates.
However, Cleveland Clinic’s patient guidance emphasizes that research remains mixed. The medical center notes that inversion may provide short-term relief but probably does not offer effective long-term treatment for chronic low back pain. Most supporting studies involve small sample sizes and limited follow-up periods.
For clinical traction, the evidence base shows similar limitations. No recent large-scale randomized trials directly compare motorized decompression tables to inversion therapy. Chiropractic sources argue that controlled traction provides superior outcomes, but these claims appear primarily in practice-oriented materials rather than independent comparative research.
The practical reality: both methods show promise for selected patients, but neither demonstrates overwhelming superiority in head-to-head comparisons. The Newcastle study’s 46% surgery reduction represents the most compelling outcome data available in 2026.
Safety Profiles: Critical Contraindications
Inversion therapy creates significant physiological changes. The inverted position increases pressure in the skull and eyes, raising intraocular and intracranial pressure. This mechanism makes inversion potentially dangerous for specific populations.
Absolute contraindications for inversion tables:
- ❌ Glaucoma or other eye diseases
- ❌ Uncontrolled hypertension
- ❌ Heart disease or stroke history
- ❌ Pregnancy
- ❌ Herniated discs with severe symptoms
- ❌ Osteoporosis or bone fragility
- ❌ Cerebral sclerosis
Clinical traction carries fewer cardiovascular risks because patients remain horizontal. However, improper force application can aggravate disc herniations or nerve compression. Professional supervision reduces these risks but doesn’t eliminate them entirely.
WebMD highlights that inversion injuries often result from operator error—users who invert too steeply, stay inverted too long, or ignore contraindications. Understanding who should not use an inversion table prevents serious complications.

Cost Analysis: Investment vs. Ongoing Expenses
Inversion Table Economics
Quality inversion tables range from $200 for basic models to $500 for premium units with additional features. This one-time investment provides unlimited sessions over the equipment’s lifespan (typically 5-10 years with proper maintenance).
Total cost breakdown:
- Initial purchase: $200-$500
- Annual maintenance: $0-$50
- Per-session cost: $0 (after initial investment)
- 5-year total: $200-$750
Users gain complete scheduling flexibility. Sessions can occur daily, multiple times per day, or as needed for symptom management. No appointment scheduling, travel time, or co-pays required.
For detailed guidance on selecting equipment, review our inversion table buying guide to match features with your specific needs.
Clinical Traction Costs
Professional traction therapy involves per-session fees ranging from $50 to $200, depending on location, provider credentials, and insurance coverage. Standard treatment protocols require 15-20 sessions.
Total cost breakdown:
- Per-session fee: $50-$200
- Standard protocol: 15-20 sessions
- Treatment course total: $750-$4,000
- Insurance coverage: Variable (often partial)
- 5-year total: $2,000-$8,000+ (if multiple courses needed)
Insurance coverage varies significantly. Some plans cover traction as part of physical therapy benefits, while others classify it as experimental or alternative treatment. Patients often face substantial out-of-pocket expenses even with insurance.
The cost differential becomes more pronounced for chronic conditions requiring ongoing management. Inversion table users can maintain long-term protocols without additional expenses, while clinical traction patients face recurring fees for each treatment course.
When Each Method Delivers Optimal Results
Best Candidates for Inversion Tables
Inversion therapy works best for patients with lumbar disc disease and sciatica who meet strict safety criteria. The Newcastle study’s success occurred specifically in this population—not in general back pain sufferers.
Ideal inversion table candidates:
- ✅ Diagnosed lumbar disc herniation or bulge
- ✅ Sciatica symptoms with nerve compression
- ✅ Normal blood pressure and eye health
- ✅ No cardiovascular disease history
- ✅ Ability to safely mount and dismount equipment
- ✅ Commitment to gradual progression protocols
Patients must follow safe usage guidelines and understand appropriate session durations. Starting with a 30-day beginner progression prevents overuse injuries and allows the body to adapt gradually.
Best Candidates for Clinical Traction
Clinical traction suits patients who need targeted decompression with professional monitoring. The controlled environment allows therapists to adjust force, angle, and duration based on real-time patient feedback.
Ideal clinical traction candidates:
- ✅ Specific vertebral level involvement requiring targeted treatment
- ✅ Complex cases needing professional assessment
- ✅ Patients with contraindications to inversion
- ✅ Those requiring integrated therapy (traction plus manual therapy, exercise)
- ✅ Individuals uncomfortable with home-based equipment
- ✅ Cases where insurance covers treatment costs
The professional supervision provides additional safety for patients with multiple health conditions. Therapists can modify protocols immediately if symptoms worsen or new issues emerge.
Combining Approaches: The Hybrid Strategy
Some patients benefit from sequential or alternating use of both methods. A common approach involves initial clinical traction to establish baseline improvement, followed by home-based inversion for maintenance.
This hybrid strategy offers several advantages:
- 🔄 Professional assessment establishes appropriate decompression parameters
- 💰 Reduces long-term clinical costs while maintaining benefits
- 📈 Allows progression from supervised to independent management
- 🎯 Combines targeted clinical treatment with flexible home sessions
However, patients must coordinate with healthcare providers to ensure compatibility. Some conditions that improve with clinical traction may still contraindicate inversion therapy due to cardiovascular or eye pressure concerns.
For those exploring complementary approaches, understanding how inversion therapy compares to physical therapy provides additional context for treatment planning.
The Verdict: Matching Method to Patient Profile
Inversion Tables vs. Traction Therapy: Which Spinal Decompression Method Delivers Better Results? The answer depends entirely on individual patient factors rather than universal superiority of either approach.
Choose inversion tables when:
- Budget constraints limit clinical treatment access
- Diagnosis involves lumbar disc disease with sciatica
- No cardiovascular, eye, or bone density contraindications exist
- Long-term maintenance protocol is needed
- Patient demonstrates ability to follow safety protocols independently
Choose clinical traction when:
- Targeted decompression of specific vertebral levels is required
- Contraindications prevent safe inversion
- Insurance coverage makes clinical treatment affordable
- Professional supervision provides necessary confidence
- Complex cases require integrated multimodal therapy
The Newcastle study’s 46% surgery reduction demonstrates inversion therapy’s potential for appropriately selected patients. However, Cleveland Clinic’s caution about limited evidence and mixed results remains valid. Neither method offers guaranteed outcomes, and both require careful patient selection.
Understanding the common myths about inversion tables helps set realistic expectations. Similarly, recognizing the potential dangers ensures informed decision-making.
Conclusion
The comparison between inversion tables and clinical traction reveals no clear universal winner. Inversion therapy offers compelling evidence for surgery reduction in lumbar disc disease patients, substantial cost advantages, and home-based convenience. Clinical traction provides targeted decompression, professional supervision, and suitability for patients with inversion contraindications.
Your next steps:
- Consult your healthcare provider to confirm your specific diagnosis and identify any contraindications to either method
- Evaluate your safety profile against the absolute contraindications for inversion therapy
- Calculate total costs including insurance coverage, equipment investment, and long-term maintenance needs
- Consider your lifestyle and whether home-based or clinical treatment fits your schedule and preferences
- Start conservatively with whichever method you choose, following gradual progression protocols
For patients who meet safety criteria and have lumbar disc disease with sciatica, inversion tables deliver proven results at a fraction of clinical traction costs. For those with contraindications or complex cases requiring targeted treatment, clinical traction provides the necessary control and professional oversight. The best choice aligns your specific diagnosis, safety profile, and financial situation with the appropriate decompression mechanism.